
The weight loss is working. Your clothes fit differently, your blood results may look better, and people have noticed. But so have you, in the mirror. Your cheeks look flatter, your temples a little hollow, and the lines around your mouth seem deeper than they were a few months ago.
Sooner or later, a question follows: if I stop the injections, will my face go back to how it was?
It is a reasonable question, and an important one, because the answer can shape a decision about your health as well as your appearance. The short version is that the face does not respond to stopping the medication. It responds to what happens to your weight, your fat and your skin afterwards. Those don’t simply run in reverse.
The short answer
Does “Ozempic face” go away if you stop the medication?
Not directly. The facial changes come from fat lost during weight loss, not from the medication acting on the face, so stopping it doesn’t reverse them on its own. In trials, most people regained a large share of their weight within a year of stopping, and some facial fullness may return with it. But regained fat doesn’t reliably go back to the same places, and stretched skin doesn’t simply tighten again. Decisions about the medication should be made with your prescribing doctor.
Why the face changes in the first place
“Ozempic face” is not a medical diagnosis. It is a popular name for the facial changes that can follow significant weight loss on GLP-1 medications such as semaglutide and tirzepatide. A systematic review of the published literature found that the changes are best explained by the weight loss itself, particularly when it is rapid or substantial, rather than by a unique drug effect on the face.¹
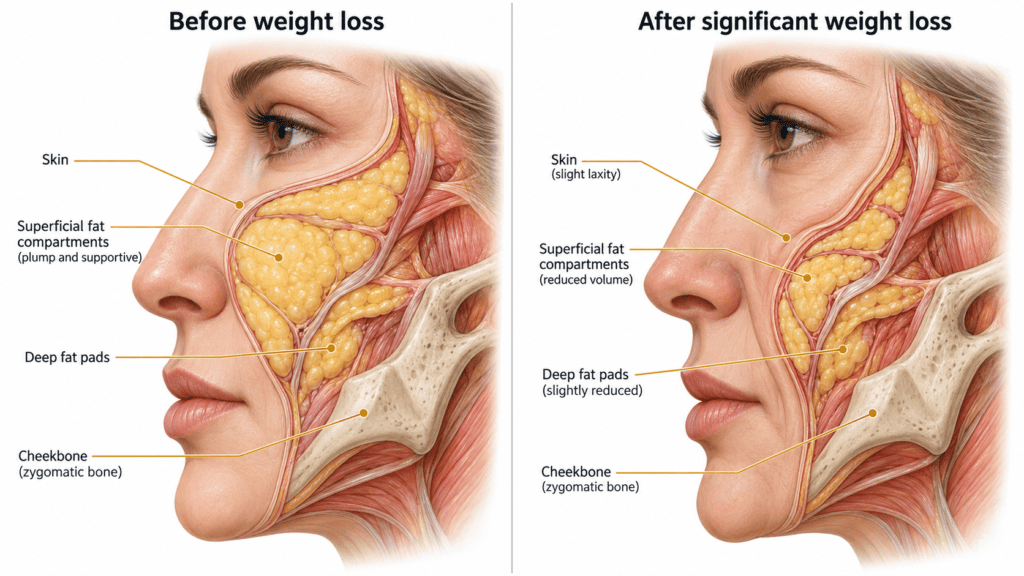
To understand whether it can reverse, it helps to know which parts of the face have changed. Three main layers are involved:
- Fat. The face is not one continuous layer of fat. It is made up of separate compartments, some just under the skin and some deeper, lying on bone. One imaging study of patients on GLP-1 medications found that midface fat compartments lost volume in proportion to weight lost, and that the superficial compartments lost more than the deep ones (roughly 11% versus 7% per 10 kg of body weight).² This is why the cheeks can look flat and “drawn” fairly early.
- Skin. When the volume underneath shrinks quickly, the skin does not always contract to match. The result is looseness, creasing and a slightly deflated look, especially along the lower face and jawline.
- The structure beneath. The facial bones and ligaments change gradually with age in everyone. Fat used to soften those changes. Once it thins, the underlying contours become more visible, which is why the face can appear to have aged faster than the rest of you.³
What happens when you stop: three scenarios
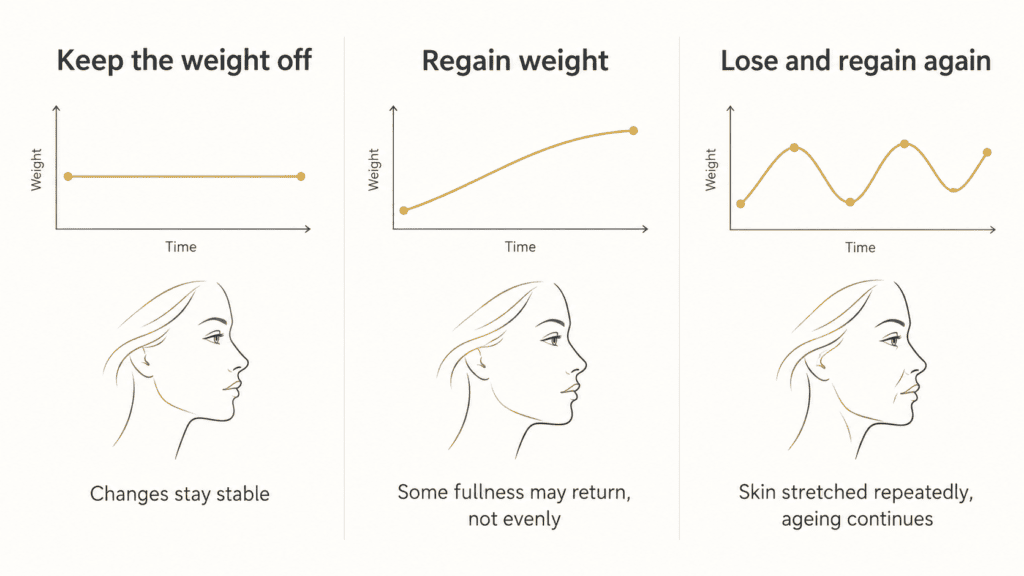
Stopping the medication does not act on the face. What it changes is appetite, and through appetite, weight. So the real question is what happens to your weight afterwards. Broadly, there are three possibilities.
1. You stop and keep the weight off
If your weight stays stable, the fat that was lost does not come back by itself. The facial changes largely remain. The skin may adapt a little over the following months, particularly in younger people with good skin quality, but hollowing and volume loss generally persist.
Many pages describe this as “permanent”. It is more accurate to say the changes are stable: they are no longer progressing, which also makes them easier to assess and plan around.
2. You stop and regain weight
This is what happens most often. In the extension of a large semaglutide trial, participants lost an average of 17.3% of their body weight over 68 weeks. One year after stopping, they had regained about two-thirds of that loss, and most of the improvements in blood pressure, blood sugar and cholesterol had moved back towards where they started.⁴ A similar pattern has been reported with tirzepatide: in an analysis of people switched to placebo after a period of treatment, 82% regained more than a quarter of the weight they had lost within a year.⁵
Some facial fullness may return as weight returns. But the face rarely goes back to exactly how it looked before, for reasons explained below.
3. You stop, regain, then try again
Some people go through more than one cycle of losing and regaining weight. Each cycle asks the skin to stretch and contract again, while time and ageing continue in the background. There is no good evidence that cycling restores the face, and it is not a strategy any doctor would recommend for that purpose.
Why regained weight doesn’t simply refill the face
It seems logical that putting weight back on would reverse the facial changes. In practice, three things get in the way.
Fat does not return to a set address. Where the body stores regained fat is influenced by genetics, age, sex and hormones, and you cannot direct it to your temples or cheeks. No study has yet measured whether the facial fat compartments refill in proportion to regained weight. Patients commonly report that weight returns to the abdomen and body more noticeably than to the face. That is an observation, not a proven rule, and it varies from person to person.
The skin is not the same skin. Skin that has stretched and then deflated does not always regain its original firmness when volume returns underneath it. Its ability to recoil depends partly on age and collagen quality, both of which decline over time.
Time has passed. Even a year or two is long enough for normal facial ageing to continue: gradual bone change, collagen decline and sun damage. The face you return to is older than the one you left.
| Layer | What weight loss did | What stopping and regaining weight may do |
|---|---|---|
| Superficial fat (cheeks, temples, under the eyes) | Deflated, often early and visibly | May partly refill, but not reliably or evenly |
| Deep fat (support near the bone) | Lost some volume, reducing support | Uncertain; not well studied |
| Skin | Stretched, then left loose as volume shrank | Rarely regains its original firmness |
| Bone and ligaments | Unchanged by the medication, but now more visible | Continue to change slowly with age |
| Overall health gains | Often improved | Tend to reverse as weight returns⁴ |
This table summarises general patterns described in the medical literature. Individual faces vary considerably.
What tends to improve on its own, and what doesn’t
Often improves with time and stable weight:
- the tired, slightly drained look some people have during the fastest phase of weight loss
- skin texture and hydration, with good nutrition, adequate protein and sun protection
- mild looseness in younger skin, which may continue to adapt over several months
Usually persists unless treated:
- temple hollowing
- flattened cheeks and a harsher lower-eyelid-to-cheek transition
- deeper folds around the nose and mouth
- jawline softening and early jowling
- loose or creased skin in the lower face and neck
This is why waiting a while after your weight settles is often sensible, but waiting indefinitely rarely changes the second list.
Stopping is a medical decision, not a cosmetic one
If you are considering stopping your medication mainly because of how your face looks, it is worth pausing on that decision.
GLP-1 medications are usually prescribed for weight-related health reasons. The evidence above shows that stopping commonly reverses much of the weight loss and the health improvements that came with it.⁴ Facial changes, by contrast, are unlikely to reverse in the same way. So stopping for cosmetic reasons risks losing the health benefit without reliably regaining the face.
- Don’t stop or change your dose without speaking to your prescribing doctor. They can tell you whether your weight-loss goal has been reached and what a safe plan for maintenance looks like.
- Ask about the pace and target of your weight loss. Facial changes tend to be more noticeable with rapid or very large losses.¹ ³ A conversation about where you are heading is often more useful than stopping abruptly.
- Look after the rest of your body composition. Adequate protein and resistance exercise help preserve muscle during weight loss. They are good for health, even if they don’t directly restore facial volume.
If your weight loss is supervised through a medical weight loss programme, your facial concerns are worth raising at the same time, so that weight goals and facial planning are considered together.
Worth knowing
The face does not respond to stopping the medication. It responds to what happens to your weight afterwards, and even then, fat, skin and the structure beneath don’t move back in step.
If your weight may still change, how does that affect treatment?
This is the part most people are never told. If you are unsure whether you will continue, stop or regain, that uncertainty should influence which treatment makes sense, not just when.
- Gradual collagen stimulation with poly-L-lactic acid (PLLA) works over weeks to months, building support across broad areas rather than adding a fixed volume to one spot. Because of this, reviewers consider it less likely to leave the face looking overfilled if weight later returns.³ An international expert consensus on patients losing weight with prescription medication also supports starting collagen stimulation during the weight-loss phase, rather than only after it ends.⁶
- Hyaluronic acid (HA) filler gives immediate, targeted correction in specific areas such as the temples, cheeks or jawline. One advantage when weight is uncertain is that HA filler can be dissolved with an enzyme if contours change.³ The trade-off is that it adds a defined volume, so the amount and placement need to account for where your weight may be heading.
- Skin-tightening treatments such as radiofrequency microneedling address laxity and texture. They don’t replace lost volume, but they don’t depend much on weight either.
Our page on collagen stimulation for “Ozempic face” explains how timing is judged in more detail, and the collagen biostimulator injections page explains how this type of treatment works.
In many cases, the best plan is a staged one: build support gradually, reassess as weight settles, and add targeted correction only where it is still needed.
What an assessment looks at
A useful consultation for facial changes after weight loss is less about choosing a product and more about understanding your situation. It usually covers:
- Your weight trajectory. How much you have lost, how quickly, whether you are still losing, and what you and your prescribing doctor are planning next.
- Which layers have changed. Superficial deflation, deeper loss of support, skin laxity, or a combination, and in which areas of the face.
- Your skin quality and age. These strongly influence how well skin adapts on its own and how it responds to treatment.
- What bothers you most. Hollow temples, a tired midface and a softer jawline are different problems with different solutions.
- Whether to treat now or wait. Sometimes the honest answer is to wait until your weight is more predictable. That is a legitimate plan, not a delay.
Key takeaway
Stopping a GLP-1 medication won’t reverse “Ozempic face” on its own, because the face changed through fat loss, not through the drug acting on it. Regaining weight may restore some fullness, but rarely the face you had before, and it usually costs the health benefits too. The better question isn’t “should I stop?” but “what has changed in my face, and what is the right plan given where my weight is heading?”
Has your face changed during weight loss?
If you are unsure whether to wait, treat or simply understand what is happening, a doctor’s assessment can help you decide with your health and your appearance both in view. We look at how your weight is changing, which layers of the face have been affected and what, if anything, makes sense to do now.
Frequently asked questions
Will my face go back to normal if I regain the weight?
Probably not completely. Some fullness may return as you regain weight, but the face rarely goes back to exactly how it looked before. Regained fat doesn’t reliably return to the same facial fat pads, skin that has stretched and deflated often doesn’t recover its original firmness, and normal ageing carries on in the meantime.
It’s completely understandable to hope that putting weight back on might undo the change, especially if you miss how your face used to look. But weight regain is an unreliable way to restore the face, and it usually costs you the health improvements you worked hard for. If the change is bothering you, it’s usually more helpful to understand exactly what has changed, whether that’s fat, skin or the support underneath, and plan around that directly.
Should I stop my weight-loss injections because of facial changes?
Not without speaking to your prescribing doctor first. Stopping usually leads to regaining much of the lost weight and losing the health benefits that came with it, while the facial changes are unlikely to reverse in the same way. You could give up the benefit without getting your old face back.
If watching your face change has made you second-guess the whole treatment, you’re not alone, and it’s a fair thing to feel. A better first step is to raise it openly with your prescriber: ask whether your goal has been reached, whether the pace of weight loss could be adjusted, and what maintenance would look like. Facial concerns can usually be assessed and treated alongside continued weight management, so it doesn’t have to be one or the other.
How quickly does weight come back after stopping?
For many people, within months. In a large semaglutide trial, participants had regained about two-thirds of the weight they had lost within one year of stopping.⁴ In a tirzepatide study, 82% of people switched to placebo regained more than a quarter of their lost weight within a year.⁵ How quickly it happens varies from person to person.
This isn’t a sign of failure or a lack of willpower. These medications work largely by reducing appetite, and when they stop, appetite tends to return. That’s why a planned maintenance approach with your prescribing doctor matters more than the moment you stop, and why it’s worth thinking about your face in the context of where your weight is likely to go next.
If I have filler and later regain weight, will I look overfilled?
It can happen, which is why your likely weight path should shape the treatment plan from the start. Filler adds a fixed volume, so if fat later returns to the same areas, the combined result can look heavier than intended. Gradual collagen stimulation is considered less likely to cause this,³ and hyaluronic acid filler can be dissolved if your contours change.
Worrying about ending up looking puffy or “done” is one of the most common reasons people hold back, and it’s a sensible concern. In practice, it’s managed by treating conservatively while your weight is still changing, prioritising underlying support rather than filling every hollow, and reviewing again once things have settled. A good plan always leaves room to adjust.
Can I treat my face while I’m still losing weight?
Often, yes. An international expert consensus supports starting gradual collagen stimulation during the weight-loss phase rather than waiting until it ends,⁶ because it builds support slowly over several months. More targeted volume correction, such as hyaluronic acid filler, is usually approached more cautiously until your weight is more predictable.
Many people assume they have to wait until the weight loss is completely over before doing anything, and sometimes waiting genuinely is the right call. But if the changes are already affecting how you feel about your face, you don’t necessarily have to put that on hold for a year or more. Our page on collagen stimulation for “Ozempic face” explains how timing is judged, and an assessment can help you decide what makes sense to start now and what is better left until later.
Does facial skin tighten on its own after weight loss?
To a degree, but usually not fully. Skin can keep adapting for several months after your weight stabilises, particularly if you are younger and your skin quality is good. Significant laxity, creasing along the lower face and jawline, and hollowing caused by lost volume tend to persist without treatment.
It’s worth giving your skin some time before judging the final result, and supporting it in the meantime with daily sun protection, adequate protein and a consistent skincare routine. If the looseness hasn’t improved once your weight has been stable for a few months, that’s a reasonable point to have it assessed. Treatments that tighten skin work differently from those that restore volume, and many faces need a combination of both.
Medical References
- Daneshgaran G, Shauly O, Gould DJ. “Ozempic face” in plastic surgery: a systematic review of the literature on GLP-1 receptor agonist mediated weight loss and analysis of public perceptions. Aesthetic Surgery Journal Open Forum. 2025;7:ojaf056. View published study
- Sharma RK, Vittetoe KL, Barna AJ, Takkouche S, et al. Radiographic midfacial volume changes in patients on GLP-1 agonists. Otolaryngology–Head and Neck Surgery. 2025;173:360–366. View published study
- Frank K, Guertler A, Hoffmeister V, et al. GLP-1–induced weight loss and the face: anatomical mechanisms and rationale for collagen-stimulating and volumizing aesthetic treatments. Dermatologic Surgery. 2026;52(6S):S55–S60. View published study
- Wilding JPH, Batterham RL, Davies M, et al. Weight regain and cardiometabolic effects after withdrawal of semaglutide: the STEP 1 trial extension. Diabetes, Obesity and Metabolism. 2022;24(8):1553–1564. View study on PubMed
- Cardiometabolic parameter change by weight regain on tirzepatide withdrawal in adults with obesity: a post hoc analysis of the SURMOUNT-4 trial. JAMA Internal Medicine. 2025. View published study
- Nikolis A, Enright KM, Fabi SG, Somenek M, et al. Consensus statements on managing aesthetic needs in prescription medication-driven weight loss patients: an international, multidisciplinary Delphi study. Journal of Cosmetic Dermatology. 2025;24:e70094.
This article is for general education and does not replace a medical consultation. It does not provide advice on starting, stopping or changing any medication. Suitability and outcomes vary between individuals.